 Quality Review
 Meet the Q&PS Team
 MedicASK Answers
 MedicASK Answers Full List
 Patient Safety Incident Report
 Loss or theft of controlled substances
 MedicASK
 Files

Data Request
- Hits: 2049


Both de-activation and de-certification signify a stop in a paramedic's authorization from the Medical Director to perform controlled medical acts. Whether de-activated or de-certified, the paramedic is no longer eligible to work as a paramedic within the certifying base hospital, except in the case of a partial clinical de-activation (see below). De-activation and de-certification may be the result of several different processes outlined below.
Most administrative de-activations are due to a paramedic's absence from work for periods greater then 90 days. After ninety days away from practice, paramedics are required to undertake a Return to Clinical Practice process and are deactivated until that process is complete. Following completion of a Return to Clinical Practice process, the RPPEO reactivates paramedics' certification.
Other potential reasons for administrative de-activation include failure to complete annual maintenance of certification activities by the deadline or failing to respond to RPPEO requests for information during audits. It's also used when the RPPEO anticipates that a paramedic plans to continue practising within the RPPEO region, but is missing some aspect of their administrative file in order to continue. In these rare cases of missing information, administrative de-activation can almost always be reversed by providing the missing administrative details.
When the Medical Director has serious concerns about the safety and quality of clinical care, they may use clinical de-activiation to limit a paramedic's activity. In the case of a full clinical de-activation, the Medical Director removes a paramedic from all clinical activities, while a partial de-activation means removing authorization for certain specified clinical activities. Following investigation of the issues, paramedics may be required to undergo remediation or other educational activities to have their certification re-reactivated. While the RPPEO maintains this process should it be required, de-activation for concerns about patient care or safety is exceedingly rare.
The RPPEO de-certifies paramedics who have left our region or who are retired from practice. There is a Ministry of Health mechanism for de-certification on the basis of patient safety concerns described in Appendix 6 of the Advanced Life Support Patient Care Standards, however, clinical decertification is extremely rare. When it does occur, it's at the recommendations of a Paramedic Practice Review Committee (PPRC). By the PPRC's review and recommendation, a paramedic who no longer meets the requirements set out in the provincial Patient Care Standards, the RPPEO's policies and/or other requirements of the Ministry of Health will be de-certified. The authorization to practice as a paramedic under the jurisdiction of the base hospital and the authorization to perform delegated controlled medical acts are thereby withdrawn.
For more details about de-activation and de-certification, see the RPPEO Certification Policy.

No one wants an administrative deactivation, but that's what the automation bot working inside MedicNET does on February 1 if you're missing requirements.
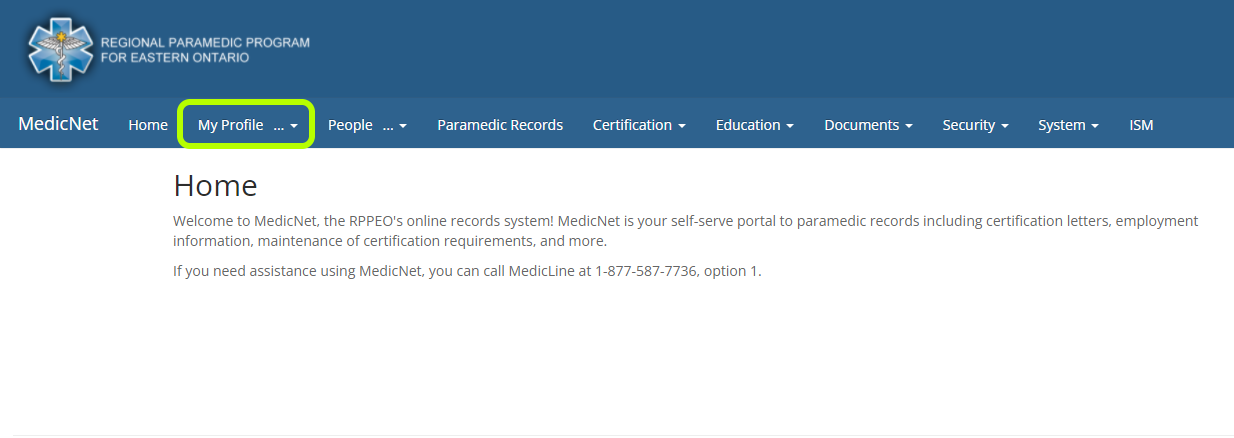
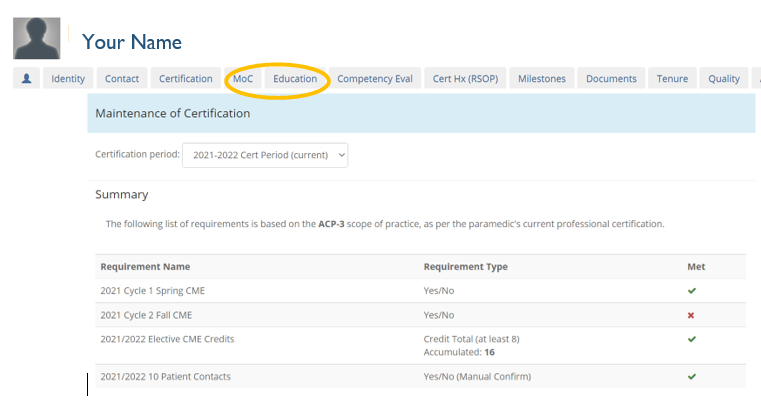
If you're in the group with administrative deactivation, check your MedicNET profile to see what you're missing. Read the FAQ below to find out how to proceed when you're ready for your paramedic certification to be re-activated.
The humans at the RPPEO are always happy to hear from you! For more about your annual CME requirements or other recertification issues, contact us at certification@rppeo.ca or 877-587-7736.
For those who have successfully re-certified for the current year, congratulations and thank you!

Go to MedicNET
Just below your name
A. January 31, each year at 23:59:59.
A: The requirements are detailed by scope of practice in the RPPEO’s Certification Policy CERT 100 available here.
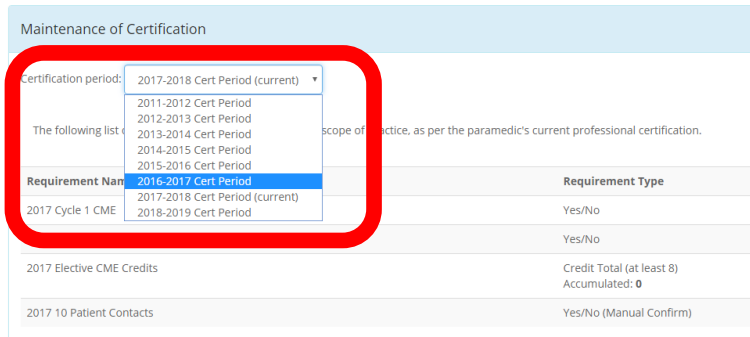
A: Please log into our website and view your profile in MedicNET (see instructions)
A. An online course is available in MedicLEARN as an approved alternative.
Title of the course: 202x-202x MOC 10 Patient Contacts Equivalency.
Direct link to MedicLEARN: 10 Patient Equivalency Course
A. You can email us at certification@rppeo.ca or call MedicLINE at 1-877-587-7736 Option 1.
A. The system will issue you an administrative deactivation letter.
A. Simply complete the missing requirement(s) online as soon as possible. Once all requirements are met, RPPEO will reactivate you.
{rseventspro type="upcoming"}
Read more …Education Events List

Thank you for completing this Online Learning Module using the RPPEO's E-Learning Portal. If you have any questions, comments or concerns please direct them to certification@rppeo.ca
We hope you have enjoyed this part of the process and welcome any feedback on what we can improve upon.
RPPEO Certification Team
Q - 1?
A - 1.
Q - 2?
A - 2.
Q - So what actually triggers a febrile seizure if it isn’t how fast the fever rises?
A - Febrile seizures appear to result from an age-dependent susceptibility of the developing brain to fever, with genetics playing an important role. The older teaching that the rapid rate of temperature rise itself causes the seizure is not well supported.
Fever is the setting in which the seizure occurs in a susceptible child; the rate of rise is not considered the direct cause. Based on current evidence, there is no way to predict occurrence, and we do not fully understand who/why yet.
Q - Does a higher fever make a febrile seizure more likely?
A - Generally, higher temperatures are associated with an increased likelihood of febrile seizures, but there is no specific temperature threshold at which a seizure will occur. One susceptible child may seize with a relatively modest fever while another may have a much higher temperature without ever having a seizure.
Higher fever is associated with risk, but the temperature alone does not predict which child will seize.
Q - If the temperature is 40°C, isn’t that dangerous by itself?
A - The temperature number alone does not determine how sick the child is. A high fever caused by infection is different from hyperthermia, such as heat stroke. With fever, assess appearance, mental status, respiratory status, perfusion, hydration and the likely source rather than treating the thermometer alone.
Distinguish fever from hyperthermia and focus on the child’s physiology and clinical appearance.
Q - Can acetaminophen or ibuprofen prevent another febrile seizure?
A - Not reliably. Antipyretics are primarily used to improve comfort, not as seizure prophylaxis. Lowering the temperature does not eliminate the child’s underlying susceptibility to febrile seizures.
Treat discomfort, not fever for the purpose of seizure prevention.
Q - Should parents alternate acetaminophen and ibuprofen?
A - Routine alternating of acetaminophen and ibuprofen is not recommended. While it may reduce fever more effectively, it has not been shown to provide meaningful clinical benefits and may increase the risk of dosing errors.
Avoid creating complicated medication schedules solely to keep the temperature down.
Q - Should we give an antipyretic to every child with a fever?
A - No. A comfortable, otherwise well-appearing child does not necessarily require an antipyretic simply because the temperature is elevated. Antipyretics are used primarily to relieve discomfort.
Treat the child’s comfort and assess the cause of the fever; do not treat a number in isolation.
Q - Will an IV fluid bolus bring the fever down?
A - Not directly. IV fluids are not antipyretics. They may be indicated for dehydration, poor perfusion or another clinical reason. A child’s temperature may change as the overall illness evolves, but fever reduction is not the reason to administer IV fluids.
Give IV fluids for an appropriate fluid or circulatory indication, not simply because a child is febrile.
Q - Can teething actually cause a fever?
A - Teething can be associated with drooling, gum discomfort, irritability and possibly a slight temperature elevation, but it should not be used to explain a true measured fever of 38.0°C or greater. A febrile child who happens to be teething still needs assessment for another cause.
Do not anchor on teething when a child has a true fever.
Q - Does a febrile seizure mean the child has epilepsy?
A - No. Febrile seizures are provoked seizures associated with fever and are distinct from epilepsy. Most children with simple febrile seizures do not go on to develop epilepsy, although risk is somewhat higher in children with certain additional risk factors.
A febrile seizure and epilepsy are not synonymous.
Q - If the child has another seizure later the same day, is it still a simple febrile seizure?
A - No. More than one seizure within 24 hours is a complex feature. Other complex features include focal seizure activity and a seizure lasting 15 minutes or longer.
Complex = focal, prolonged (≥15 minutes), or recurrent within 24 hours.
Q - If the seizure stops at 6 minutes, is it automatically a complex febrile seizure?
A - No. This is an important distinction. Any ongoing convulsive seizure requires termination regardless of time. Greater than 5 minutes or not returning to baseline between seizures is considered status epilepticus by modern seizure care definitions as spontaneous termination become less likely beyond this point, while 15 minutes is the duration criterion used to classify a febrile seizure as complex.
The 5-minute and 15-minute thresholds answer different clinical questions.
Q - What if the child is having a focal seizure — can we still treat with midazolam?
A - Yes, but a focal seizure does not meet the generalized motor seizure indication for midazolam under the medical directive. If medication is clinically indicated, the paramedic should patch to a BHP for direction, including consideration of a lower dose that may be more appropriate for focal seizure activity.
Focal seizure sometimes generalize; do not let them continue as they are uncomfortable and need to be terminated.
Q - Can we rely on SpO₂ to tell us they’re ventilating adequately after a seizure or midazolam?
A - No. SpO₂ assesses oxygenation, not ventilation. Assess respiratory rate, effort and chest rise, and use ETCO₂/capnography when available and appropriate to help trend ventilation, particularly when respiratory depression is a concern.
A normal SpO₂ does not prove adequate ventilation.
Q - If the child has a fever and seizure, when should meningitis or another serious CNS process be on our radar?
A - Concern increases with persistent altered mental status, meningeal or focal neurologic findings, petechiae or purpura, toxic appearance, poor perfusion, prolonged or focal seizures, recurrent seizures, or a history and recovery pattern that do not fit a typical simple febrile seizure.
Fever plus seizure is not automatically a benign febrile seizure; actively look for red flags.
Q - How long is a ‘normal’ postictal phase?
A - There is no single exact normal duration. What matters is the trajectory toward the child’s neurologic baseline. In pediatrics, the postictal period is usually brief, but the expected duration depends on the type of seizure. Most children return to baseline within 30 minutes to 1 hour after a simple seizure. After a simple febrile seizure, it is common for a child to be sleepy, confused, irritable, or want to sleep for a few minutes up to a few hours.
Following a prolonged seizure, multiple seizures, status epilepticus, or administration of benzodiazepines such as midazolam, the postictal period may last several hours. Trend recovery rather than relying on one fixed postictal time limit.
Q - If a seizure is clearly secondary to hypoglycemia, should the priority be treating the seizure itself or correcting the hypoglycemia?
A - The priority is rapid correction of the hypoglycemia. The risk of seizure in this case is rare (5% in one study), and most sugars were found to be less than 1.5 mmol in this case. It is important to remember to manage the seizure simultaneously (i.e. airway management).
Treat the cause, not just the symptom. In hypoglycemic seizures, anticonvulsants may stop the motor activity, but seizure activity can persist or recur until adequate glucose is restored to the brain. Correcting hypoglycemia is the key intervention. Children have smaller glycogen stores, higher metabolic demands, and are more prone to hypoglycemia during illness, fasting, vomiting, or metabolic disorders.
Q - Is IM or IN midazolam the preferred route of administration?
A - Current evidence suggests IM midazolam may provide slightly faster, more reliable seizure control, but IN midazolam offers comparable overall effectiveness with easier and faster administration (94.2% efficacy for IM and 93.3% efficacy for IN – no significant difference overall). Early treatment and correct dosing remain more important than the route itself.
The American Epilepsy Society guideline considers both intranasal and intramuscular midazolam effective options when IV access is not available in seizures. Do not delay medication administration for IV access.
Read more …Frequently Asked Questions

